Medications · September 29, 2026 · Memios · 21 min read
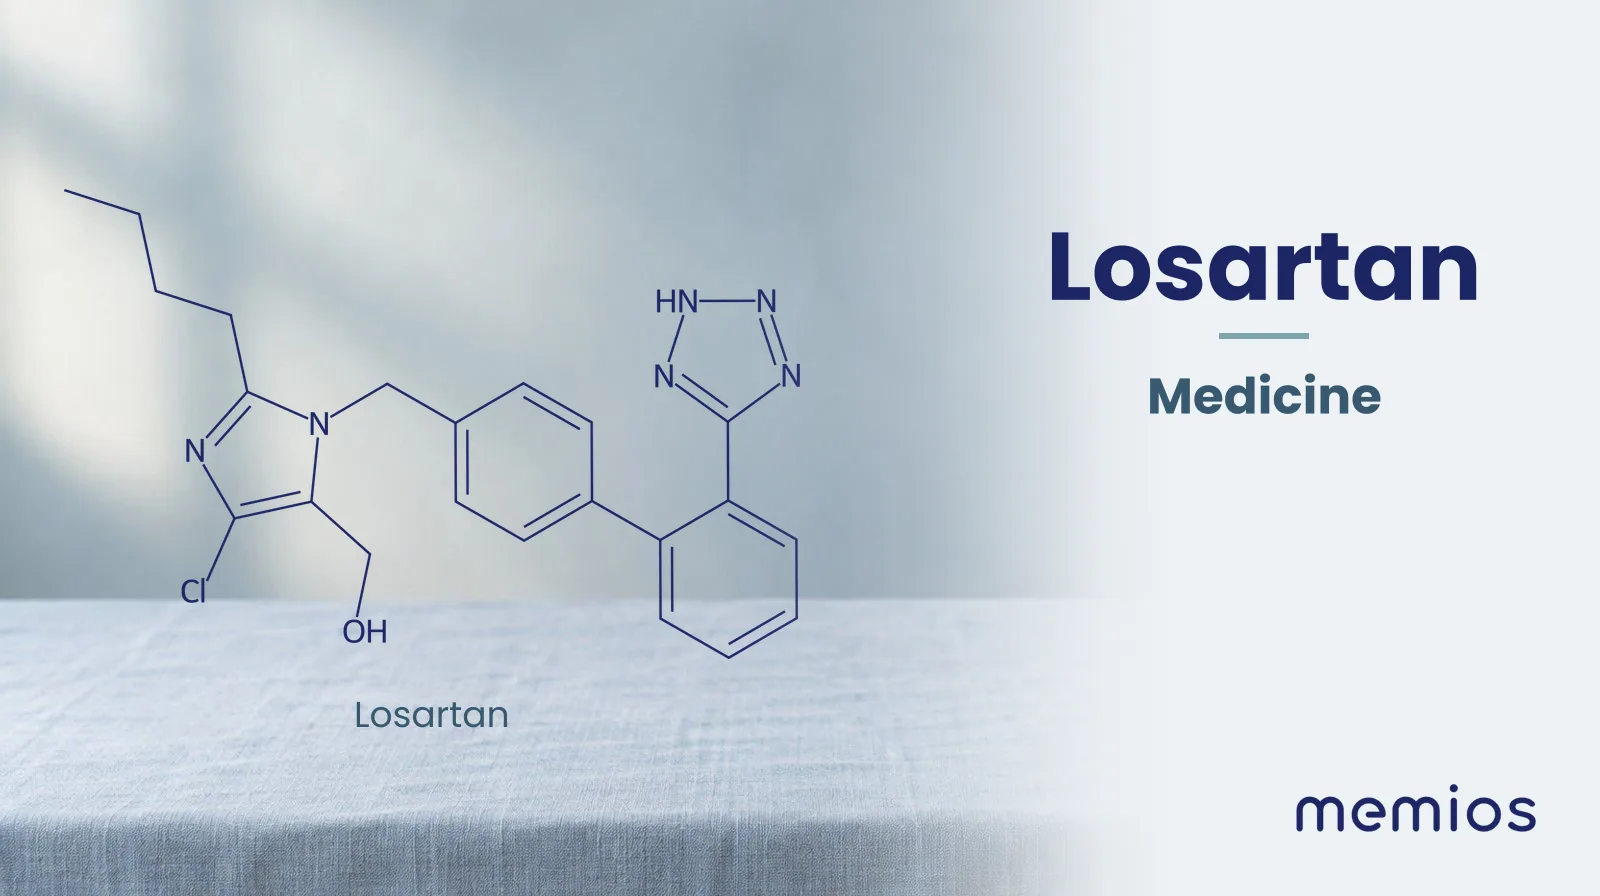
Losartan
Well established. Losartan lowers blood pressure.
TLDR
- Boxed warning: When pregnancy is detected, discontinue losartan potassium tablets as soon as possible.
- Well established. Losartan lowers blood pressure.
- What it is: Losartan is a prescription angiotensin II receptor blocker.
- Main use: High blood pressure (well supported).
- Other approved uses: Stroke risk reduction in hypertension with left ventricular hypertrophy (well supported); Diabetic kidney disease in type 2 diabetes (well supported).
- Uses NOT supported by research: Marfan syndrome (aortic root).
- Recommended dose (official position): The dose is set by the prescriber. As a position, the US label (revised November 2018) gives a usual starting dose of 50 mg once daily.
- Studied dose (a trial dose, not a recommendation): RENAAL gave losartan 50 to 100 mg once daily on top of conventional treatment. Findings citing that trial: 1 for.
- Upper limit: As a position, the label gives a maximum of 100 mg once daily.
- What goes wrong: 5 findings on harm. SPRINT's more intensive blood-pressure target came with more serious adverse events of low blood pressure, fainting, electrolyte problems and acute kidney injury.
- Interactions: 4 recorded, including Potassium supplements and potassium-containing salt substitutes, Other drugs that raise potassium, Potassium salt substitute (trial context), Lithium.
- Common myth: The 2018-2019 recalls mean all losartan is contaminated.
What it is
Losartan is a prescription angiotensin II receptor blocker. It stops angiotensin II, a hormone that narrows blood vessels, from binding its AT1 receptor.
What the research says
Losartan lowers blood pressure. In LIFE it prevented more cardiovascular events, mainly strokes, than atenolol in people with an enlarged heart. In RENAAL it slowed kidney decline in type 2 diabetic kidney disease but did not change deaths. ARBs cause less cough than ACE inhibitors. It can raise potassium and change kidney function, and carries the fetal toxicity boxed warning. Some lots were recalled in 2019 for a nitrosamine impurity.
Evidence grade: Well established.
How it works
Drug class: Angiotensin II receptor blocker (ARB)
Losartan and its active metabolite block the AT1 receptor, so angiotensin II cannot narrow blood vessels or trigger aldosterone release. Blood pressure falls as a result. (Source 1)
Boxed warning
When pregnancy is detected, discontinue losartan potassium tablets as soon as possible.
(Source 2)
What it is used for
- Lowers blood pressure; class-wide trial data link lowering pressure to fewer cardiovascular events. A Cochrane review found ARBs not different from ACE inhibitors on deaths, but noted ARBs have not had placebo-controlled hypertension outcome trials. Evidence: established. (Source 3)
- In LIFE, losartan-based treatment reduced the combined endpoint and stroke more than atenolol. The label says this benefit may not apply to Black patients. Evidence: established. (Source 4)
- In RENAAL, losartan reduced doubling of creatinine and end-stage kidney disease against placebo but did not change deaths. Evidence: established. (Source 5)
- In a trial of 608 children and young adults with Marfan syndrome, losartan was no better than atenolol: the change in aortic-root size and the rates of aortic surgery, dissection and death did not differ significantly between the two drugs. Evidence: not-supported. (Source 6)
Interactions
- Potassium supplements and potassium-containing salt substitutes (label): The label's patient counselling section tells patients on losartan not to use potassium supplements or potassium-containing salt substitutes without consulting their healthcare provider. (Source 7)
- Other drugs that raise potassium (label): Taking losartan with other drugs that raise blood potassium may push potassium too high; the label says to monitor potassium in such patients. (Source 8)
- Potassium salt substitute (trial context) (clinical trial): A large salt-substitute trial saw no rise in serious high-potassium events, but excluded people with kidney disease or at risk of high potassium. (Source 9)
- Lithium (label): Lithium levels and toxicity can rise; the label says to monitor lithium. (Source 10)
Stopping it
- A 2025 Cochrane review update in older people (all blood-pressure drugs, not this drug alone) found that stopping blood-pressure drugs may make little or no difference to death, hospital admission or stroke, but may raise blood pressure; effects on heart attack and on side effects were very uncertain. (Source 11)
- The review rated the evidence low to very low certainty, mainly because the studies were small and events were few. (Source 11)
- In the STOP-ACEi trial of people with advanced, progressing chronic kidney disease, stopping ACE inhibitors or ARBs did not slow the fall in kidney function compared with continuing them. (Source 12)
What goes wrong
In 2019 the FDA reported a recall of 87 lots of losartan made by Hetero Labs because of NMBA, a nitrosamine impurity it called a known animal and potential human carcinogen. (Source 13)
- Official position, Certainty not rated.
- Size: 87 recalled lots.
- Who: US patients on the recalled lots.
- How long: n/a.
- Result: NMBA levels above FDA interim acceptable intake limits in recalled lots; no human cancer rate given.
- Funding: n/a (regulator)
The recalled losartan potassium tablets made by Hetero Labs and distributed by Camber Pharmaceuticals contain the impurity, N-Nitroso-N-methyl-4-aminobutyric acid (NMBA). The impurity is a known animal and potential human carcinogen.
The FDA said nitrosamines in ARBs may come from specific manufacturing chemicals and conditions, or from reusing materials such as solvents. (Source 14)
- Official position, Certainty not rated.
- Size: n/a.
- Who: n/a.
- How long: n/a.
- Result: Mechanism of contamination, not a health outcome.
- Funding: n/a (regulator)
The FDA's evaluation suggests that the nitrosamines found in ARBs may be generated when specific chemicals and reaction conditions are present in the manufacturing process of the drug's API, and may also result from the reuse of materials, such as solvents.
The label warns that drugs blocking the renin-angiotensin system can cause changes in kidney function, including acute kidney failure; people whose kidney function depends partly on that system (for example with renal artery stenosis, chronic kidney disease, severe heart failure or volume depletion) may be at particular risk, and kidney function should be monitored periodically in them. (Source 15)
- Official position, Certainty not rated.
- Size: n/a.
- Who: label population.
- How long: n/a.
- Result: No rate in passage.
- Funding: n/a (regulatory label)
Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the renin-angiotensin system (e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, or volume depletion) may be at particular risk of developing acute renal failure on losartan potassium tablets. Monitor renal function periodically in these patients.
The label warns that taking losartan with other drugs that raise potassium may cause high potassium (hyperkalaemia), and says to monitor potassium in such patients. (Source 8)
- Official position, Certainty not rated.
- Size: n/a.
- Who: label population.
- How long: n/a.
- Result: No rate in passage.
- Funding: n/a (regulatory label)
Coadministration of losartan with other drugs that raise serum potassium levels may result in hyperkalemia. Monitor serum potassium in such patients.
SPRINT's more intensive blood-pressure target came with more serious adverse events of low blood pressure, fainting, electrolyte problems and acute kidney injury. (Source 16)
- Randomized trial, Moderate certainty.
- Size: 9,361 participants.
- Who: adults at high cardiovascular risk without diabetes.
- How long: median 3.26 years.
- Result: Higher rates of serious hypotension, syncope, electrolyte abnormalities and acute kidney injury in the intensive group; injurious falls not higher.
- Funding: National Institutes of Health.
Rates of serious adverse events of hypotension, syncope, electrolyte abnormalities, and acute kidney injury or failure, but not of injurious falls, were higher in the intensive-treatment group than in the standard-treatment group.
What the evidence supports
In LIFE, losartan-based treatment led to fewer deaths, heart attacks and strokes combined than atenolol-based treatment, for similar blood pressure lowering, in people with left ventricular hypertrophy. (Source 4)
- Randomized trial, Moderate certainty.
- Size: 9,193 participants.
- Who: adults 55-80 with hypertension and ECG-diagnosed LVH.
- How long: at least 4 years.
- Result: Primary endpoint 23.8 vs 27.9 per 1000 patient-years (RR 0.87, 0.77-0.98); stroke 232 vs 309 (0.75, 0.63-0.89)
- Funding: not stated in the abstract we read.
The primary composite endpoint occurred in 508 losartan (23.8 per 1000 patient-years) and 588 atenolol patients (27.9 per 1000 patient-years; relative risk 0.87, 95% CI 0.77-0.98, p=0.021).
In RENAAL, losartan slowed progression of kidney disease in type 2 diabetes with nephropathy against placebo, but had no effect on death. (Source 5)
- Randomized trial, Moderate certainty.
- Size: 1,513 patients.
- Who: adults with type 2 diabetes and nephropathy.
- How long: mean 3.4 years.
- Result: Primary composite 327 vs 359 (risk reduction 16%); doubling of creatinine -25%; end-stage renal disease -28%; no effect on death.
- Funding: not stated in the abstract we read.
Losartan reduced the incidence of a doubling of the serum creatinine concentration (risk reduction, 25 percent; P=0.006) and end-stage renal disease (risk reduction, 28 percent; P=0.002) but had no effect on the rate of death.
A Cochrane review of head-to-head trials found no evidence of a difference between ARBs (such as losartan) and ACE inhibitors for death or cardiovascular events, and slightly fewer withdrawals for side effects with ARBs, mainly because ACE inhibitors cause more dry cough. (Source 3)
- Systematic review, Moderate certainty.
- Size: 9 studies, 11,007 participants.
- Who: people with primary hypertension.
- How long: mean 4.1 years for withdrawal outcome.
- Result: Mortality RR 0.98 (0.88-1.10); withdrawal for adverse effects RR 0.83 favouring ARBs, ARR 1.8%, NNT 55 over 4.1 years. Mortality evidence moderate, cardiovascular events low (GRADE).
- Funding: not stated.
There was no evidence of a difference between ACE inhibitors and ARBs for total mortality (risk ratio (RR) 0.98; 95% confidence interval (CI) 0.88 to 1.10), total cardiovascular events (RR 1.07; 95% CI 0.96 to 1.19), or cardiovascular mortality (RR 0.98; 95% CI 0.85 to 1.13). Conversely, a high level of evidence indicated a slightly lower incidence of WDAE for ARBs as compared with ACE inhibitors (RR 0.83; 95% CI 0.74 to 0.93; absolute risk reduction (ARR) 1.8%, number needed to treat for an additional beneficial outcome (NNTB) 55 over 4.1 years), mainly attributable to a higher incidence of dry cough with ACE inhibitors.
In a network meta-analysis of randomised trials, ACE inhibitors had about three times the risk of cough of ARBs such as losartan. (Source 17)
- Meta-analysis, Certainty not rated.
- Size: 135 RCTs, 45,420 patients.
- Who: patients in ACE inhibitor trials.
- How long: trial durations varied.
- Result: RR ACEI vs ARB 3.2 (2.91-3.51)
- Funding: not stated in the abstract we read.
ACEI had more incidences of cough than ARB (RR 3.2; 95% CI: 2.91, 3.51),
Across 48 randomised trials of blood-pressure-lowering drugs of all classes, the rate of major cardiovascular events was lower in treated groups, in people with and without prior cardiovascular disease. (Source 18)
- Meta-analysis, High certainty.
- Size: 344,716 participants in 48 randomised trials.
- Who: adults in blood-pressure-lowering trials, with and without previous cardiovascular disease.
- How long: median 4.15 years.
- Result: Without previous CVD: 31.9 vs 25.9 major CV events per 1000 person-years (comparator vs intervention). With previous CVD: 39.7 vs 36.0 per 1000 person-years. HR per 5 mm Hg systolic reduction 0.91 (0.89-0.94) and 0.89 (0.86-0.92).
- Funding: British Heart Foundation, UK NIHR, Oxford Martin School (independent)
In participants without previous cardiovascular disease at baseline, the incidence rate for developing a major cardiovascular event per 1000 person-years was 31·9 (95% CI 31·3–32·5) in the comparator group and 25·9 (25·4–26·4) in the intervention group.
The same individual-participant meta-analysis found that each 5 mm Hg fall in systolic pressure was linked to about a 10% lower risk of major cardiovascular events, regardless of prior disease; this is a class-wide result, not specific to one drug. (Source 19)
- Meta-analysis, High certainty.
- Size: 344,716 participants in 48 randomised trials.
- Who: adults in blood-pressure-lowering trials.
- How long: median 4.15 years.
- Result: About 10% relative reduction per 5 mm Hg systolic reduction.
- Funding: British Heart Foundation, UK NIHR, Oxford Martin School (independent)
a 5 mm Hg reduction of systolic blood pressure reduced the risk of major cardiovascular events by about 10%, irrespective of previous diagnoses of cardiovascular disease,
In SPRINT, targeting systolic pressure below 120 rather than below 140 mm Hg in high-risk adults without diabetes lowered the rate of the primary cardiovascular outcome; this tests treatment intensity, using any drugs, not this drug specifically. (Source 16)
- Randomized trial, Moderate certainty.
- Size: 9,361 participants.
- Who: adults aged 50+ at high cardiovascular risk without diabetes, systolic 130 mm Hg or higher.
- How long: median 3.26 years (stopped early)
- Result: Primary outcome 1.65% vs 2.19% per year (HR 0.75, 0.64-0.89); all-cause mortality HR 0.73 (0.60-0.90). Absolute difference about 0.54 percentage points per year.
- Funding: National Institutes of Health.
The intervention was stopped early after a median follow-up of 3.26 years owing to a significantly lower rate of the primary composite outcome in the intensive-treatment group than in the standard-treatment group (1.65% per year vs. 2.19% per year; hazard ratio with intensive treatment, 0.75; 95% confidence interval [CI], 0.64 to 0.89; P<0.001).
The Hygia trial reported that taking blood-pressure drugs at bedtime rather than on waking was followed by markedly fewer major cardiovascular events (see the disagreement with the TIME trial). (Source 20)
- Randomized trial, Low certainty.
- Size: 19,084 patients.
- Who: hypertensive patients in Spanish primary care.
- How long: 6.3-year median follow-up.
- Result: Adjusted HR for primary CVD outcome 0.55 (95% CI 0.50-0.61)
- Funding: not stated in the abstract we read.
Routine ingestion by hypertensive patients of ≥1 prescribed BP-lowering medications at bedtime, as opposed to upon waking, results in improved ABP control (significantly enhanced decrease in asleep BP and increased sleep-time relative BP decline, i.e. BP dipping) and, most importantly, markedly diminished occurrence of major CVD events.
What the evidence does not support
In LIFE, losartan did not significantly reduce cardiovascular death or heart attack compared with atenolol; the gain was in stroke. (Source 4)
- Randomized trial, Moderate certainty.
- Size: 9,193 participants.
- Who: adults 55-80 with hypertension and LVH.
- How long: at least 4 years.
- Result: CV death 0.89 (0.73-1.07); MI 1.07 (0.88-1.31)
- Funding: not stated in the abstract we read.
204 losartan and 234 atenolol patients died from cardiovascular disease (0.89, 0.73-1.07, p=0.206); 232 and 309, respectively, had fatal or non-fatal stroke (0.75, 0.63-0.89, p=0.001); and myocardial infarction (non-fatal and fatal) occurred in 198 and 188, respectively (1.07, 0.88-1.31, p=0.491).
In children and young adults with Marfan syndrome, the yearly change in aortic-root size relative to body size did not differ significantly between losartan and atenolol; the aortic root shrank relative to body size in both groups, and rates of aortic surgery, dissection and death did not differ. (Source 6)
- Randomized trial, Moderate certainty.
- Size: 608 participants.
- Who: ages 6 months to 25 years with Marfan syndrome and aortic-root z score above 3.0.
- How long: 3 years.
- Result: Aortic-root z-score change -0.107 (losartan) vs -0.139 (atenolol) SD units per year, P=0.08; both slopes significantly below zero; no significant difference in 3-year surgery, dissection, death or the composite.
- Funding: National Heart, Lung, and Blood Institute and others.
The baseline-adjusted rate of change in the mean (±SE) aortic-root z score did not differ significantly between the atenolol group and the losartan group (-0.139±0.013 and -0.107±0.013 standard-deviation units per year, respectively; P=0.08). Both slopes were significantly less than zero, indicating a decrease in the aortic-root diameter relative to body-surface area with either treatment. The 3-year rates of aortic-root surgery, aortic dissection, death, and a composite of these events did not differ significantly between the two treatment groups.
The UK TIME trial found no difference in major cardiovascular outcomes between evening and morning dosing of usual blood-pressure drugs. (Source 21)
- Randomized trial, Moderate certainty.
- Size: 21,104 participants.
- Who: adults with hypertension in the UK (90.5% White)
- How long: median 5.2 years.
- Result: Primary endpoint 3.4% evening vs 3.7% morning; unadjusted HR 0.95 (0.83-1.10); p=0.53. Open-label, blinded end-point design.
- Funding: British Heart Foundation.
Evening dosing of usual antihypertensive medication was not different from morning dosing in terms of major cardiovascular outcomes.
Where the evidence is mixed
The same Cochrane review warned that its head-to-head results cannot be used to conclude that ARBs share the outcome benefits ACE inhibitors showed against placebo, because ARBs have not been tested in placebo-controlled hypertension outcome trials. (Source 22)
- Systematic review, Moderate certainty.
- Size: 9 studies, 11,007 participants.
- Who: people with primary hypertension.
- How long: mean 4.1 years for withdrawal outcome.
- Result: No effect size in this passage; see the companion finding for mortality RR 0.98 (0.88-1.10) and withdrawal RR 0.83.
- Funding: not stated.
Although ACE inhibitors have shown efficacy in these outcomes over placebo, our results cannot be used to extrapolate the same conclusion for ARBs directly, which have not been studied in placebo-controlled trials for hypertension.
Where the research disagrees
Whether taking blood-pressure drugs at bedtime prevents more heart attacks and strokes than morning dosing
- Hermida and colleagues (Hygia Chronotherapy Trial, 2020), randomised endpoint trial, 19,084 patients, one research network: Routine ingestion by hypertensive patients of ≥1 prescribed BP-lowering medications at bedtime, as opposed to upon waking, results in improved ABP control (significantly enhanced decrease in asleep BP and increased sleep-time relative BP decline, i.e. BP dipping) and, most importantly, markedly diminished occurrence of major CVD events. (Source 20)
- Mackenzie and colleagues (TIME study, 2022), randomised, open-label, blinded end-point trial, 21,104 participants: Evening dosing of usual antihypertensive medication was not different from morning dosing in terms of major cardiovascular outcomes. (Source 21)
Whether ARBs such as losartan can stand in for ACE inhibitors on hard outcomes
- Li, Heran and Wright (Cochrane, 2014), systematic review of 9 head-to-head trials: Although ACE inhibitors have shown efficacy in these outcomes over placebo, our results cannot be used to extrapolate the same conclusion for ARBs directly, which have not been studied in placebo-controlled trials for hypertension. (Source 22)
- LIFE investigators (2002), randomised trial against atenolol, 9,193 participants: Losartan prevents more cardiovascular morbidity and death than atenolol for a similar reduction in blood pressure and is better tolerated. (Source 23)
How much
- Reference intake: The dose is set by the prescriber. As a position, the US label (revised November 2018) gives a usual starting dose of 50 mg once daily. (Source 24)
- Upper limit: As a position, the label gives a maximum of 100 mg once daily. (Source 24)
- Studied: RENAAL gave losartan 50 to 100 mg once daily on top of conventional treatment. (Source 5)
- Studied: LIFE gave once-daily losartan-based treatment for at least 4 years. (Source 4)
A common belief, and what the research shows
The belief: The 2018-2019 recalls mean all losartan is contaminated.
What the research shows: The FDA announcement described specific recalled lots from one manufacturer: "Hetero Labs Ltd. in India has announced a recall of 87 lots of losartan potassium tablets (25 mg, 50 mg and 100 mg)."
Questions and answers
What is it?
Losartan is a prescription angiotensin II receptor blocker (ARB). It and its active metabolite block the receptor that the blood-vessel-narrowing hormone angiotensin II acts on. (Source 1)
What does it do in the body?
By blocking the AT1 receptor, it stops angiotensin II from narrowing blood vessels and from triggering aldosterone release. (Source 1)
Is it good or bad for you?
In people with high blood pressure and an enlarged heart (the LIFE trial), losartan prevented more cardiovascular illness and death than atenolol for a similar fall in blood pressure, and was better tolerated. Its harms are set out in the findings. (Source 23)
How do you get more of it?
The prescriber sets the dose. As a regulatory position, the label gives a usual starting dose of 50 mg once daily and a maximum of 100 mg once daily. (Source 24)
If it is harmful, what reduces it?
For the losartan lots recalled over a nitrosamine impurity, the FDA told patients to keep taking their medicine until their doctor or pharmacist gave them a replacement or a different treatment. (Source 25)
Why might someone be low in it or missing it?
Does not apply. Losartan is a prescription medicine, not a nutrient or a substance the body makes, so there is no deficiency state; the label describes it as a treatment. (Source 26)
We searched: DailyMed label indications and mechanism sections; Cochrane and trial literature on this drug
Which whole foods contain it or feed it?
No food contains losartan. The food-related issue is potassium: the label tells patients not to use potassium supplements or potassium-containing salt substitutes without consulting their healthcare provider. (Source 7)
What happens if you do not have it?
Nobody needs losartan in the way they need a nutrient; it matters only for people it is prescribed to. In a Cochrane review of older people whose blood-pressure drugs were stopped, blood pressure may rise. (Source 11)
How can you test for it?
The sources we read describe no routine test of losartan levels. The label says to monitor blood potassium periodically. (Source 27)
References
- US National Library of Medicine, DailyMed (FDA-approved label). Losartan potassium tablets (Torrent Pharmaceuticals, repackaged by Direct_Rx) - prescribing information, SPL setid 90a2b710-574a-4f49-e053-2995a90ad2a9, revised November 2018. 2018. Read the source
- US National Library of Medicine, DailyMed (FDA-approved label). Losartan potassium tablets (Torrent Pharmaceuticals, repackaged by Direct_Rx) - prescribing information, SPL setid 90a2b710-574a-4f49-e053-2995a90ad2a9, revised November 2018. 2018. Read the source
- Cochrane Database of Systematic Reviews. Angiotensin converting enzyme (ACE) inhibitors versus angiotensin receptor blockers for primary hypertension. 2014. PMID 25148386, DOI 10.1002/14651858.CD009096.pub2. Read the source
- Lancet. Cardiovascular morbidity and mortality in the Losartan Intervention For Endpoint reduction in hypertension study (LIFE): a randomised trial against atenolol. 2002. PMID 11937178, DOI 10.1016/s0140-6736(02)08089-3. Read the source
- New England Journal of Medicine. Effects of losartan on renal and cardiovascular outcomes in patients with type 2 diabetes and nephropathy. 2001. PMID 11565518, DOI 10.1056/nejmoa011161. Read the source
- New England Journal of Medicine. Atenolol versus losartan in children and young adults with Marfan's syndrome. 2014. PMID 25405392, DOI 10.1056/NEJMoa1404731. Read the source
- US National Library of Medicine, DailyMed (FDA-approved label). Losartan potassium tablets (Torrent Pharmaceuticals, repackaged by Direct_Rx) - prescribing information, SPL setid 90a2b710-574a-4f49-e053-2995a90ad2a9, revised November 2018. 2018. Read the source
- US National Library of Medicine, DailyMed (FDA-approved label). Losartan potassium tablets (Torrent Pharmaceuticals, repackaged by Direct_Rx) - prescribing information, SPL setid 90a2b710-574a-4f49-e053-2995a90ad2a9, revised November 2018. 2018. Read the source
- American College of Cardiology. Salt Substitute and Stroke Study (SSaSS) - American College of Cardiology trial summary of Neal B et al., Effect of Salt Substitution on Cardiovascular Events and Death, NEJM 2021. 2021. DOI 10.1056/NEJMoa2105675. Read the source
- US National Library of Medicine, DailyMed (FDA-approved label). Losartan potassium tablets (Torrent Pharmaceuticals, repackaged by Direct_Rx) - prescribing information, SPL setid 90a2b710-574a-4f49-e053-2995a90ad2a9, revised November 2018. 2018. Read the source
- Cochrane Database of Systematic Reviews. What are the effects of stopping blood pressure medications in older people? (Cochrane review CD012572, withdrawal of antihypertensive drugs in older people, 2025 update). 2025. Read the source
- New England Journal of Medicine. Renin-angiotensin system inhibition in advanced chronic kidney disease. 2022. PMID 36326117, DOI 10.1056/NEJMoa2210639. Read the source
- US Food and Drug Administration. FDA provides update on its ongoing investigation into ARB drug products; reports on finding of a new nitrosamine impurity in certain lots of losartan and product recall. 2019. Read the source
- US Food and Drug Administration. FDA provides update on its ongoing investigation into ARB drug products; reports on finding of a new nitrosamine impurity in certain lots of losartan and product recall. 2019. Read the source
- US National Library of Medicine, DailyMed (FDA-approved label). Losartan potassium tablets (Torrent Pharmaceuticals, repackaged by Direct_Rx) - prescribing information, SPL setid 90a2b710-574a-4f49-e053-2995a90ad2a9, revised November 2018. 2018. Read the source
- New England Journal of Medicine. A Randomized Trial of Intensive versus Standard Blood-Pressure Control. 2015. PMID 26551272, DOI 10.1056/nejmoa1511939. Read the source
- The Journal of Clinical Hypertension. Angiotensin-converting enzyme inhibitor induced cough compared with placebo, and other antihypertensives: A systematic review, and network meta-analysis. 2023. DOI 10.1111/jch.14695. Read the source
- Lancet. Pharmacological blood pressure lowering for primary and secondary prevention of cardiovascular disease across different levels of blood pressure: an individual participant-level data meta-analysis. 2021. PMID 33933205, DOI 10.1016/S0140-6736(21)00590-0. Read the source
- Lancet. Pharmacological blood pressure lowering for primary and secondary prevention of cardiovascular disease across different levels of blood pressure: an individual participant-level data meta-analysis. 2021. PMID 33933205, DOI 10.1016/S0140-6736(21)00590-0. Read the source
- European Heart Journal. Bedtime hypertension treatment improves cardiovascular risk reduction: the Hygia Chronotherapy Trial. 2020. PMID 31641769, DOI 10.1093/eurheartj/ehz754. Read the source
- Lancet. Cardiovascular outcomes in adults with hypertension with evening versus morning dosing of usual antihypertensives in the UK (TIME Study): a prospective, randomised, open-label, blinded end-point clinical trial. 2022. PMID 36240838, DOI 10.1016/S0140-6736(22)01786-X. Read the source
- Cochrane Database of Systematic Reviews. Angiotensin converting enzyme (ACE) inhibitors versus angiotensin receptor blockers for primary hypertension. 2014. PMID 25148386, DOI 10.1002/14651858.CD009096.pub2. Read the source
- Lancet. Cardiovascular morbidity and mortality in the Losartan Intervention For Endpoint reduction in hypertension study (LIFE): a randomised trial against atenolol. 2002. PMID 11937178, DOI 10.1016/s0140-6736(02)08089-3. Read the source
- US National Library of Medicine, DailyMed (FDA-approved label). Losartan potassium tablets (Torrent Pharmaceuticals, repackaged by Direct_Rx) - prescribing information, SPL setid 90a2b710-574a-4f49-e053-2995a90ad2a9, revised November 2018. 2018. Read the source
- US Food and Drug Administration. FDA provides update on its ongoing investigation into ARB drug products; reports on finding of a new nitrosamine impurity in certain lots of losartan and product recall. 2019. Read the source
- US National Library of Medicine, DailyMed (FDA-approved label). Losartan potassium tablets (Torrent Pharmaceuticals, repackaged by Direct_Rx) - prescribing information, SPL setid 90a2b710-574a-4f49-e053-2995a90ad2a9, revised November 2018. 2018. Read the source
- US National Library of Medicine, DailyMed (FDA-approved label). Losartan potassium tablets (Torrent Pharmaceuticals, repackaged by Direct_Rx) - prescribing information, SPL setid 90a2b710-574a-4f49-e053-2995a90ad2a9, revised November 2018. 2018. Read the source