Medications · September 29, 2026 · Memios · 14 min read
Lorazepam
Well established. Lorazepam sedates and damps down anxiety, and it stops seizures.
TLDR
- Boxed warning: Limit dosages and durations to the minimum required.
- Well established. Lorazepam sedates and damps down anxiety, and it stops seizures.
- What it is: Lorazepam is a benzodiazepine, a class of drugs that act on the GABA-A receptor in the brain. Pharmacology reviews describe it as binding to benzodiazepine receptors on postsynaptic GABA-A ligand-gated chloride channel neurons, which amplifies the brain's main inhibitory signal.
- Main use: Anxiety disorders and short-term relief of anxiety symptoms (limited evidence).
- Other approved uses: Status epilepticus (convulsive seizures that do not stop) (well supported); Premedication before anaesthesia, for sedation, anxiety relief or amnesia (limited evidence).
- Off-label uses (not on the FDA label): Alcohol withdrawal, delirium, agitation, catatonia, insomnia, panic disorder, vertigo and anticipatory nausea with chemotherapy (evidence not rated).
- Recommended dose (official position): There is no reference intake for a controlled prescription medicine; dosing is set by the prescriber. As a position, the manufacturer's label (DailyMed, revised 5 August 2025) states the usual range is 2 to 6 mg/day in divided doses.
- Studied dose (a trial dose, not a recommendation): The prehospital status epilepticus trial gave a single intravenous dose of lorazepam, diazepam or placebo administered by paramedics; termination of seizures was judged on arrival at the emergency department. Findings citing that trial: 2 for.
- Upper limit: As a position, the same label states the daily dosage may vary from 1 to 10 mg/day, with the largest dose taken before bedtime.
- What goes wrong: 5 findings on harm. Benzodiazepine use is associated with a substantially higher risk of hip fracture in older people.
- Interactions: 4 recorded, including Opioid painkillers, Alcohol and other central nervous system depressants, Valerian (Valeriana officinalis) and similar sedating herbal products, Other medicines and substances used alongside, including illicit substances.
- Common myth: Lorazepam is a long-term treatment for anxiety, and the main risk is just feeling sleepy.
What it is
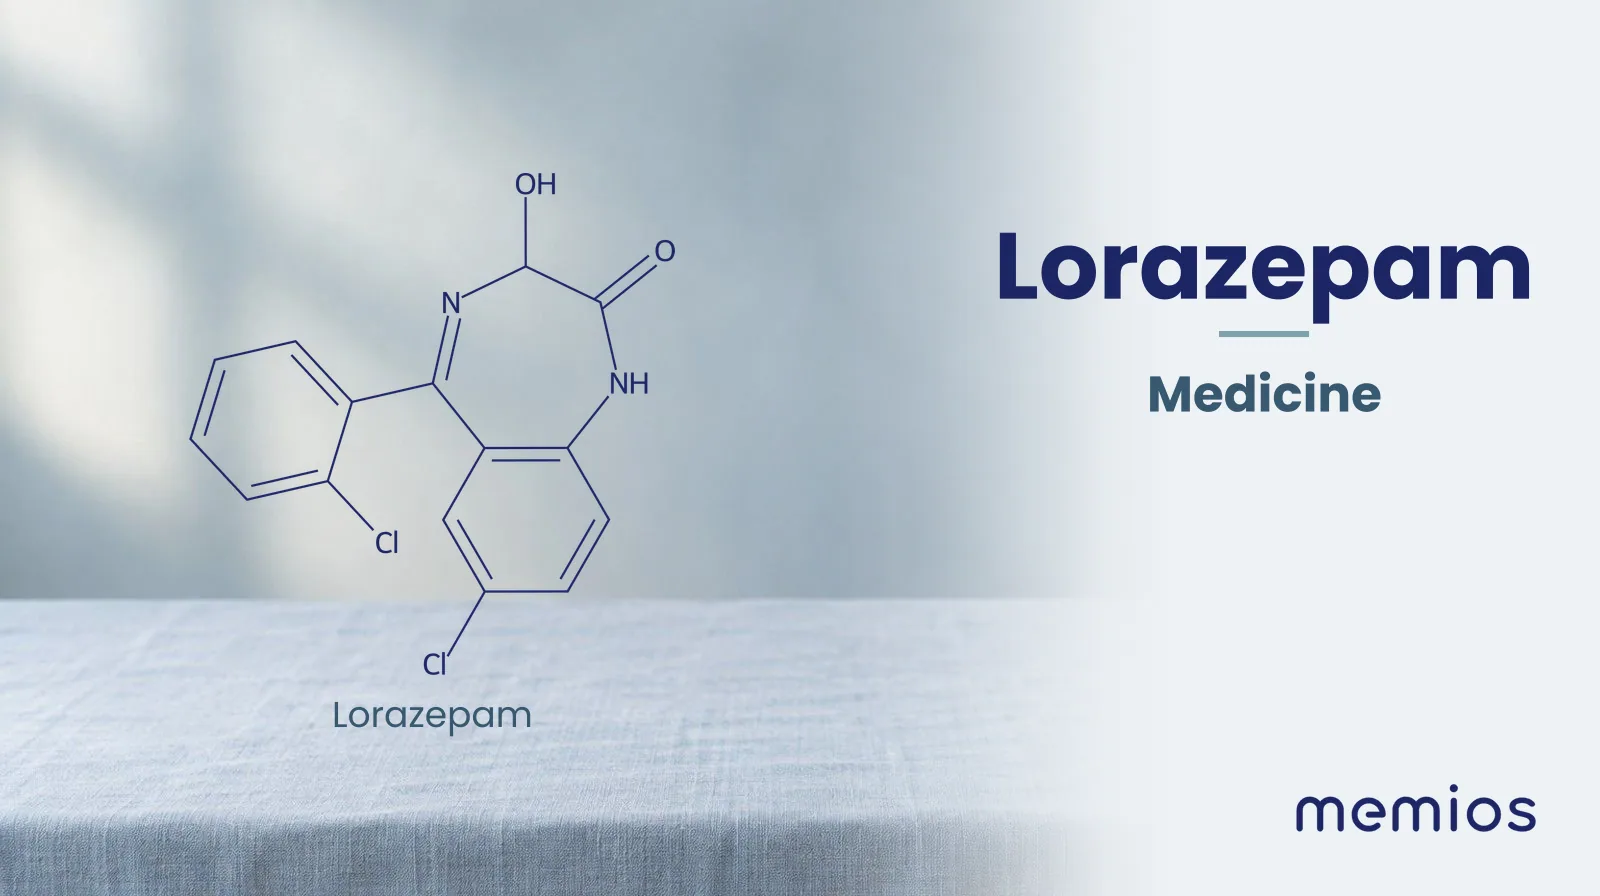
Lorazepam is a benzodiazepine, a class of drugs that act on the GABA-A receptor in the brain. Pharmacology reviews describe it as binding to benzodiazepine receptors on postsynaptic GABA-A ligand-gated chloride channel neurons, which amplifies the brain's main inhibitory signal. It is a scheduled controlled substance in the United States and comes as tablets, an oral concentrate and an injection. The tablet label carries a boxed warning covering opioid co-use, abuse and addiction, and dependence and withdrawal.
What the research says
Lorazepam sedates and damps down anxiety, and it stops seizures. The best controlled evidence is in status epilepticus, where a randomised placebo-controlled prehospital trial showed clear benefit. For anxiety the evidence is short-term: the manufacturer's own label states that effectiveness beyond four months has not been assessed in systematic studies. Set against this are well-documented harms - sedation in about one in six people in trials, a roughly 50% higher risk of hip fracture in older people in observational studies, physical dependence with a withdrawal syndrome the label calls potentially life-threatening, and fatal respiratory depression when combined with opioids.
Evidence grade: Well established.
How it works
Drug class: Benzodiazepine (GABA-A receptor positive allosteric modulator); intermediate-acting anxiolytic, sedative and anticonvulsant
Lorazepam attaches to a site on the GABA-A receptor, the main brake in the brain. When GABA is present, the drug makes that brake work harder, letting more chloride into the nerve cell and making it less likely to fire. That is why it calms anxiety, causes drowsiness, relaxes muscle and stops seizures. (Source 1)
Boxed warning
WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS. Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of these drugs for patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Follow patients for signs and symptoms of respiratory depression and sedation. The use of benzodiazepines, including lorazepam tablets, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes. Before prescribing lorazepam and throughout treatment, assess each patient's risk for abuse, misuse, and addiction. The continued use of benzodiazepines, including lorazepam tablets, may lead to clinically significant physical dependence. The risks of dependence and withdrawal increase with longer treatment duration and higher daily dose. Abrupt discontinuation or rapid dosage reduction of lorazepam tablets after continued use may precipitate acute withdrawal reactions, which can be life-threatening. To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam tablets or reduce the dosage.
(Source 2)
What it is used for
- This is the labelled indication for the tablets, but it is explicitly a short-term one: the label records that effectiveness beyond four months has not been assessed in systematic clinical studies. We could not reach the main GAD meta-analyses within this run, so the strength of the short-term effect is not quantified here. Evidence: limited. (Source 2)
- In a randomised, double-blind prehospital trial, seizures had stopped by arrival at hospital in 59.1% of patients given lorazepam versus 21.1% given placebo, and respiratory or circulatory complications were no more common than with placebo. Evidence: established. (Source 3)
- A labelled use of the injection. We did not retrieve comparative outcome trials for this indication in this search. Evidence: limited. (Source 1)
- A pharmacology reference lists these as recognised off-label uses of lorazepam. We did not retrieve the underlying trials for each of them in this run, so this entry records that the uses exist, not how strong the evidence is for any one of them. Evidence: unknown. (Source 1)
Interactions
- Opioid painkillers (label): The combination can stop breathing. This is the first component of the boxed warning. (Source 2)
- Alcohol and other central nervous system depressants (label): Alcohol adds to the sedating effect, deepening drowsiness and the risk of stopping breathing. (Source 2)
- Valerian (Valeriana officinalis) and similar sedating herbal products (theoretical): The concern is additive sedation rather than a proven pharmacokinetic effect; the US National Center for Complementary and Integrative Health states valerian should not be combined with alcohol or sedatives, while noting the sleep-inducing effect itself is unproven. (Source 4)
- Other medicines and substances used alongside, including illicit substances (label): The label ties abuse and misuse of benzodiazepines specifically to combined use with other drugs and alcohol, and to worse outcomes when that happens. (Source 2)
Stopping it
- The label's instruction is that stopping is done by gradual reduction, not abruptly, because abrupt stopping after continued use can produce withdrawal reactions that are potentially fatal. (Source 2)
- Dependence and withdrawal risk are dose- and duration-dependent according to the boxed warning. (Source 2)
- A meta-analysis of discontinuation strategies in long-term users found that adding psychotherapy to a systematic taper raised the success rate, and that a minimal intervention followed by systematic discontinuation was supported. (Source 5)
What goes wrong
Benzodiazepine use is associated with a substantially higher risk of hip fracture in older people. (Source 6)
- Meta-analysis, Low certainty.
- Size: 18 studies (9 case-control, 9 cohort); individual study sizes ranged from 500 to 906,422.
- Who: older adults.
- How long: varies by study; the greatest risk was seen with short-term use.
- Result: benzodiazepines RR 1.52 (95% CI 1.37-1.68); Z-drugs RR 1.90 (95% CI 1.68-2.13); short-term benzodiazepine use RR 2.40 (95% CI 1.88-3.05)
- Funding: not stated in the abstract read.
Both BNZ, and Z-drug use respectively, were significantly associated with an increased risk of hip fracture (RR = 1.52, 95% CI 1.37–1.68
The review's own conclusion is that the association between benzodiazepines and hip fracture in older people is strongly supported. (Source 6)
- Meta-analysis, Low certainty.
- Size: 18 observational studies.
- Who: older people.
- How long: not stated.
- Result: see pooled relative risks above; all included studies were observational, so confounding by indication cannot be excluded.
- Funding: not stated in the abstract read.
There is strong evidence that both BNZ and Z-drugs are associated with an increased risk of hip fracture in the older person
Sedation is the commonest adverse effect in the manufacturer's pooled data, and it gets more likely with age. (Source 2)
- Official position, Certainty not rated.
- Size: not stated on the label page read.
- Who: patients in the manufacturer's clinical experience with lorazepam.
- How long: not stated.
- Result: sedation 15.9%, dizziness 6.9%, weakness 4.2%, unsteadiness 3.4%; no placebo comparator given on the label.
- Funding: not applicable (manufacturer label)
The most frequent adverse reaction to lorazepam was sedation (15.9%), followed by dizziness (6.9%), weakness (4.2%), and unsteadiness (3.4%).
Continued use causes physical dependence, and stopping abruptly can cause withdrawal reactions that can kill. (Source 2)
- Official position, Certainty not rated.
- Size: not applicable.
- Who: people taking benzodiazepines continuously.
- How long: risk rises with longer treatment and higher daily dose.
- Result: no rate given in the boxed warning.
- Funding: not applicable (manufacturer label)
Abrupt discontinuation or rapid dosage reduction of lorazepam tablets after continued use may precipitate acute withdrawal reactions, which can be life-threatening.
Taken with opioids, benzodiazepines can cause fatal respiratory depression. (Source 2)
- Official position, Certainty not rated.
- Size: not applicable.
- Who: people prescribed both a benzodiazepine and an opioid.
- How long: not stated.
- Result: no rate given; the label reserves combined prescribing for patients with no adequate alternative.
- Funding: not applicable (manufacturer label)
Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death.
What the evidence supports
In out-of-hospital status epilepticus, lorazepam stopped seizures in far more patients than placebo. (Source 3)
- Randomized trial, Moderate certainty.
- Size: 205 patients randomised in the trial (percentages as reported)
- Who: adults with out-of-hospital status epilepticus treated by paramedics.
- How long: single treatment; outcome assessed on arrival at the emergency department.
- Result: terminated in 59.1% with lorazepam, 42.6% with diazepam, 21.1% with placebo (P=0.001); adjusted odds ratio lorazepam versus placebo 4.8 (95% CI 1.9 to 13.0)
- Funding: not stated in the abstract read.
Status epilepticus had been terminated on arrival at the emergency department in more patients treated with lorazepam (59.1 percent) or diazepam (42.6 percent) than patients given placebo (21.1 percent) (P= 0.001).
In that trial, breathing and circulation complications were no more common with lorazepam than with placebo. (Source 3)
- Randomized trial, Moderate certainty.
- Size: as above.
- Who: adults with out-of-hospital status epilepticus.
- How long: after study treatment was given.
- Result: 10.6% lorazepam, 10.3% diazepam, 22.5% placebo (P=0.08)
- Funding: not stated in the abstract read.
The rates of respiratory or circulatory complications after the study treatment was administered were 10.6 percent for the lorazepam group, 10.3 percent for the diazepam group, and 22.5 percent for the placebo group (P=0.08).
Adding a psychological intervention to a gradual taper improves the chance of getting off long-term benzodiazepines. (Source 5)
- Meta-analysis, Low certainty.
- Size: not stated in the structured abstract read.
- Who: long-term benzodiazepine users.
- How long: varies by trial.
- Result: odds ratio 1.8 (95% CI 1.1 to 2.9) for systematic discontinuation with psychotherapy versus systematic discontinuation alone.
- Funding: not stated in the abstract read.
A higher success rate was found for systematic discontinuation with psychotherapy compared with systematic discontinuation alone (OR 1.8, 95% CI: 1.1, 2.9)
What the evidence does not support
Lorazepam has not been shown to work beyond about four months, because it has not been tested that way. (Source 2)
- Official position, Certainty not rated.
- Size: not applicable.
- Who: people taking lorazepam for anxiety.
- How long: more than 4 months.
- Result: no effect estimate exists; the label records the absence of systematic long-term studies.
- Funding: not applicable (manufacturer label)
The effectiveness of lorazepam in long-term use, that is, more than 4 months, has not been assessed by systematic clinical studies.
Where the research disagrees
Whether benzodiazepines have a place in treating anxiety beyond the short term
- Manufacturer label (DailyMed, revised 5 August 2025), regulatory position, not a trial result: The effectiveness of lorazepam in long-term use, that is, more than 4 months, has not been assessed by systematic clinical studies. (Source 2)
- Pharmacology reference listing current practice, textbook chapter summarising practice, no stated review method; the same chapter lists continuing off-label use for insomnia, panic disorder, delirium and agitation: Short-term (4 months) relief of anxiety symptoms associated with anxiety disorders (Source 1)
How much
- Reference intake: There is no reference intake for a controlled prescription medicine; dosing is set by the prescriber. As a position, the manufacturer's label (DailyMed, revised 5 August 2025) states the usual range is 2 to 6 mg/day in divided doses. (Source 2)
- Upper limit: As a position, the same label states the daily dosage may vary from 1 to 10 mg/day, with the largest dose taken before bedtime. The boxed warning separately directs that dosages and durations be limited to the minimum required. (Source 2)
- Studied: The prehospital status epilepticus trial gave a single intravenous dose of lorazepam, diazepam or placebo administered by paramedics; termination of seizures was judged on arrival at the emergency department. (Source 3)
A common belief, and what the research shows
The belief: Lorazepam is a long-term treatment for anxiety, and the main risk is just feeling sleepy.
What the research shows: The label itself says the drug has not been shown to work long term: "The effectiveness of lorazepam in long-term use, that is, more than 4 months, has not been assessed by systematic clinical studies." And the risks are not limited to drowsiness: the boxed warning records that "The continued use of benzodiazepines, including lorazepam tablets, may lead to clinically significant physical dependence.", and observational data put the hip fracture risk about 50% higher in older users.
Questions and answers
What is it?
Lorazepam is a benzodiazepine, a prescription sedative and anti-anxiety drug that is also used to stop prolonged seizures. It is a controlled substance in the United States. In tablet form it is licensed for anxiety. (Source 2)
What does it do in the body?
It attaches to benzodiazepine sites on the GABA-A receptor, the brain's main inhibitory switch, and makes that inhibition stronger. The result is sedation, reduced anxiety, muscle relaxation and suppression of seizure activity. (Source 1)
Is it good or bad for you?
It depends entirely on the setting. In a seizure that will not stop, a single dose is clearly better than nothing and was not more dangerous than placebo for breathing in the trial. Taken continuously for anxiety it has no demonstrated benefit beyond about four months and carries dependence, withdrawal, sedation and fracture risk. (Source 3)
How do you get more of it?
It is available only on prescription and is a controlled substance, so there is no other route to it. The label's stated usual range is 2 to 6 mg a day in divided doses, with the largest dose at bedtime; the actual dose is a prescriber's decision. (Source 2)
If it is harmful, what reduces it?
When lorazepam is doing harm, the literature's answer is a gradual taper rather than stopping suddenly, because abrupt withdrawal after continued use can be life-threatening. A meta-analysis found that adding psychological support to a taper roughly doubled the odds of success in long-term users. (Source 2)
Why might someone be low in it or missing it?
This question does not apply in the usual sense: lorazepam is not something the body makes or takes in from food. What the literature does describe is tolerance and dependence developing with continued use, so the same dose has less effect and stopping becomes hard. (Source 2)
Which whole foods contain it or feed it?
No food contains lorazepam or feeds it. Food and drink matter here as interactions: alcohol adds to the sedation, and sedating herbal products such as valerian are advised against alongside sedatives for the same reason. (Source 4)
What happens if you do not have it?
For someone who has never taken it, nothing: there is no deficiency state. For someone taking it regularly, stopping abruptly is the risk, because acute withdrawal reactions can be severe and even fatal, which is why a taper is specified. (Source 2)
How can you test for it?
Lorazepam shows up on benzodiazepine urine drug screens, but no test tells you whether the drug is helping. What the evidence tracks instead is effect and harm over time, and the label notes that the incidence of sedation and unsteadiness rises with age, which is what clinicians watch for. (Source 2)
We searched: We searched for validated monitoring or therapeutic drug level testing for lorazepam via WebSearch alongside the StatPearls lorazepam chapter and the DailyMed label; neither describes a validated monitoring test, so we report only what the label says is observed clinically.
References
- StatPearls Publishing, NCBI Bookshelf (Ghiasi N, Bhansali RK, Marwaha R). Lorazepam (StatPearls). 2024. PMID 30422485. Read the source
- US National Library of Medicine, DailyMed (manufacturer label, Sun Pharmaceutical Industries, Inc.; SPL last updated 5 August 2025, and the Medication Guide within it carries "Revised: 01/2023"). LORAZEPAM tablet - prescribing information (DailyMed). 2025. Read the source
- The New England Journal of Medicine (Alldredge BK, Gelb AM, Isaacs SM, et al.); copy read on regulations.gov. A Comparison of Lorazepam, Diazepam, and Placebo for the Treatment of Out-of-Hospital Status Epilepticus. 2001. PMID 11547716, DOI 10.1056/NEJMoa002141. Read the source
- US National Center for Complementary and Integrative Health (NCCIH). Valerian: Usefulness and Safety. 2025. Read the source
- Database of Abstracts of Reviews of Effects (DARE), NCBI Bookshelf; primary study Oude Voshaar RC et al., British Journal of Psychiatry 2006;189:213-220. Strategies for discontinuing long-term benzodiazepine use: meta-analysis (DARE structured abstract). 2006. PMID 16946355. Read the source
- PLOS ONE. Benzodiazepines, Z-drugs and the risk of hip fracture: A systematic review and meta-analysis. 2017. PMID 28448593, DOI 10.1371/journal.pone.0174730. Read the source