Medications · September 30, 2026 · Memios · 28 min read
Lamotrigine
For epilepsy the evidence is strong and consistent: added to other drugs in drug-resistant focal epilepsy it nearly doubles the chance of halving seizure frequency (RR 1.80, moderate certainty).
TLDR
- Boxed warning: However, cases have occurred in the absence of these factors.
- Well established. For epilepsy the evidence is strong and consistent: added to other drugs in drug-resistant focal epilepsy it nearly doubles the chance of halving seizure frequency (RR 1.80, moderate certainty).
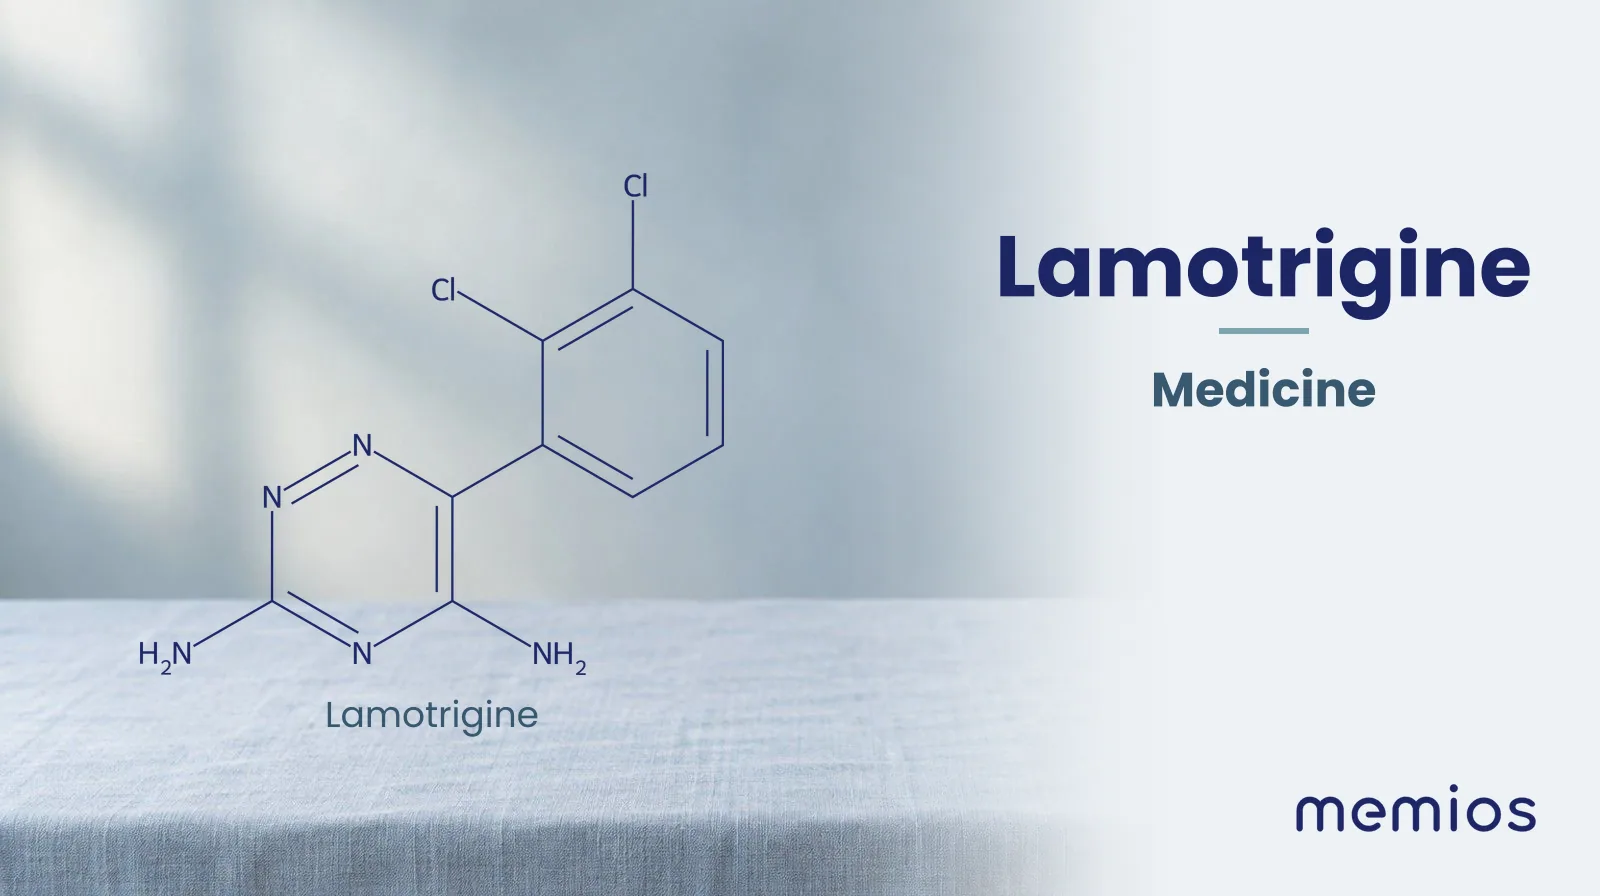
- What it is: Lamotrigine is a synthetic phenyltriazine anticonvulsant taken as tablets, chewable tablets or orally disintegrating tablets.
- Main use: Add-on treatment of drug-resistant focal (partial-onset) seizures (well supported).
- Other approved uses: First-line monotherapy for newly diagnosed focal epilepsy (well supported); Add-on treatment of drug-resistant generalised tonic-clonic seizures (limited evidence); Maintenance treatment of bipolar I disorder and treatment of bipolar depression (limited evidence).
- Uses NOT supported by research: Augmentation for treatment-resistant unipolar (major) depression.
- Recommended dose (official position): There is no reference intake for a medicine. Dose is set by the prescriber and is escalated slowly because of the rash risk, which the label states is concentrated in the first 2 to 8 weeks.
- Studied dose (a trial dose, not a recommendation): The add-on epilepsy trials pooled by Cochrane enrolled 1806 participants in total; the doses used in individual trials were not given in the review summary we could reach, so no studied dose is reported here. Findings citing that trial: 1 for, 1 against, 1 on harm.
- Upper limit: As a position, the US labelling states that for bipolar disorder doses above 200 mg/day are not recommended, because trials of up to 400 mg/day as monotherapy showed no additional benefit over 200 mg/day.
- What goes wrong: 5 findings on harm. In SANAD II a third of people starting lamotrigine reported adverse reactions, fewer than on either comparator drug.
- Interactions: 3 recorded, including Valproate (valproic acid, divalproex), Estrogen-containing oral contraceptives, Abrupt withdrawal of lamotrigine itself.
- Common myth: Lamotrigine is an antidepressant, so it should help ordinary (unipolar) depression too.
What it is
Lamotrigine is a synthetic phenyltriazine anticonvulsant taken as tablets, chewable tablets or orally disintegrating tablets. It is approved in the United States both as epilepsy treatment and for maintenance treatment of bipolar I disorder to delay new mood episodes. It is cleared mainly by glucuronidation, which is why valproate and estrogen-containing contraceptives change its blood levels.
What the research says
For epilepsy the evidence is strong and consistent: added to other drugs in drug-resistant focal epilepsy it nearly doubles the chance of halving seizure frequency (RR 1.80, moderate certainty), and in the SANAD II trial of newly diagnosed focal epilepsy levetiracetam failed to match it and the per-protocol analysis put lamotrigine ahead of both comparators. For mood disorder the picture is weaker: an independent individual-patient meta-analysis of five manufacturer-funded trials found a modest benefit in bipolar depression with a number needed to treat of 11, and for treatment-resistant unipolar depression the reviewed evidence was largely uncontrolled and showed no difference on depression rating scales. The main harm is serious rash, which the boxed warning quantifies, along with ataxia, dizziness, diplopia and nausea, all more common than placebo.
Evidence grade: Well established.
How it works
Drug class: Phenyltriazine antiepileptic drug; voltage-sensitive sodium channel blocker (mood stabiliser)
Lamotrigine blocks voltage-sensitive sodium channels, which steadies over-excitable nerve membranes and cuts the release of excitatory messengers such as glutamate. That is the accepted explanation for its anti-seizure effect; the label states the mechanism behind its effect in bipolar disorder has not been established. (Source 1)
Boxed warning
Lamotrigine can cause serious rashes requiring hospitalization and discontinuation of treatment. The incidence of these rashes, which have included Stevens-Johnson syndrome, is approximately 0.3% to 0.8% in pediatric patients (aged 2 to 17 years) and 0.08% to 0.3% in adults receiving lamotrigine. One rash-related death was reported in a prospectively followed cohort of 1,983 pediatric patients (aged 2 to 16 years) with epilepsy taking lamotrigine as adjunctive therapy. In worldwide postmarketing experience, rare cases of toxic epidermal necrolysis and/or rash-related death have been reported in adult and pediatric patients, but their numbers are too few to permit a precise estimate of the rate.
(Source 2)
What it is used for
- Cochrane pooled 12 trials with 1322 participants and found lamotrigine probably increases the chance of halving seizure frequency (RR 1.80, 95% CI 1.45 to 2.23, moderate certainty), with more ataxia, dizziness, nausea and double vision than placebo and no more withdrawals overall. Evidence: established. (Source 3)
- In the independent SANAD II randomised trial, 990 people in its focal epilepsy arm, levetiracetam failed to meet the non-inferiority criterion against lamotrigine for time to 12-month remission while zonisamide met it, and the per-protocol analysis found lamotrigine superior to both. Lamotrigine had the fewest adverse reactions (33% versus 44% and 45%), and the trial concluded its findings do not support levetiracetam or zonisamide as first-line treatments. Evidence: established. (Source 4)
- Only three small trials totalling 300 participants exist. They suggest nearly double the chance of halving seizure frequency (RR 1.88) but Cochrane rated this low certainty and said the review provides insufficient information to inform clinical practice. Evidence: limited. (Source 5)
- An independent individual-patient meta-analysis of five manufacturer-funded trials (1072 patients) found a modest benefit over placebo in bipolar depression, with a number needed to treat of 11 on the HRSD and 13 on the MADRS. The approved indication is maintenance, to delay new mood episodes. Evidence: limited. (Source 6)
- A systematic review of ten studies (289 patients, only one randomised) found no difference on HAM-D, MADRS or GAF scores and concluded there was little evidence to guide this use. Evidence: not-supported. (Source 7)
Interactions
- Valproate (valproic acid, divalproex) (label): Valproate blocks the liver pathway that clears lamotrigine, so blood levels more than double. This raises the risk of the serious rash the boxed warning describes, which is why escalation schedules are slower on valproate. (Source 8)
- Estrogen-containing oral contraceptives (label): Estrogen-containing contraceptives speed up lamotrigine's clearance and lower its blood level, so seizure or mood control can fade; levels can rise again in the pill-free week. (Source 9)
- Abrupt withdrawal of lamotrigine itself (label): Stopping suddenly rather than tapering can bring seizures back or make them more frequent in people with epilepsy. (Source 10)
Stopping it
- The label's position, in its Withdrawal Seizures section, is that lamotrigine should not be stopped abruptly: unless safety requires faster withdrawal, the dose is tapered over at least two weeks, roughly halving each week, because in epilepsy stopping can increase seizure frequency. (Source 10)
- The reason the label gives for tapering, in the same Withdrawal Seizures section, is the possibility that seizures become more frequent when the drug is removed; it also records 2 patients in bipolar disorder trials who had seizures shortly after abrupt withdrawal. (Source 10)
What goes wrong
The same Cochrane review found lamotrigine probably raises the risk of ataxia more than threefold, and also raises dizziness, nausea and double vision, against placebo. (Source 3)
- Systematic review, Moderate certainty.
- Size: 1525 participants across 12 trials for ataxia; 1768 across 13 trials for dizziness; 1486 across 12 studies for nausea; 944 across 3 trials for diplopia.
- Who: people with drug-resistant focal epilepsy taking lamotrigine as add-on therapy.
- How long: treatment phases eight to 36 weeks.
- Result: ataxia RR 3.34 (99% CI 2.01 to 5.55); dizziness RR 1.76 (99% CI 1.28 to 2.43); nausea RR 1.81 (99% CI 1.22 to 2.68); diplopia RR 3.79 (99% CI 2.15 to 6.68); all moderate-certainty.
- Funding: Cochrane review, independent; included trials largely industry sponsored.
Lamotrigine compared with placebo is probably associated with a greater risk of ataxia (RR 3.34, 99% Cl 2.01 to 5.55; 12 trials; 1525 participants; moderate-certainty evidence), dizziness (RR 1.76, 99% Cl 1.28 to 2.43; 13 trials; 1768 participants; moderate-certainty evidence), nausea (RR 1.81, 99% CI 1.22 to 2.68; 12 studies, 1486 participants; moderate-certainty evidence), and diplopia (RR 3.79, 99% Cl 2.15 to 6.68; 3 trials, 944 participants; moderate-certainty evidence).
In that review's 26-participant cross-over trial, rash and fatigue were reported only in the lamotrigine condition and not on placebo. (Source 5)
- Systematic review, Low certainty.
- Size: the cross-over trial within the review, 26 participants.
- Who: children and adults with drug-resistant generalised tonic-clonic seizures.
- How long: cross-over trial periods.
- Result: rash in seven lamotrigine participants and zero placebo participants; fatigue in five lamotrigine participants and zero placebo participants.
- Funding: Cochrane review, independent.
Rash (seven lamotrigine participants; zero placebo participants) and fatigue (five lamotrigine participants; zero placebo participants) were the most frequently reported adverse effects.
In SANAD II a third of people starting lamotrigine reported adverse reactions, fewer than on either comparator drug. (Source 11)
- Randomized trial, High certainty.
- Size: 990 participants in the focal epilepsy trial.
- Who: people with newly diagnosed focal epilepsy.
- How long: at least 2 years of follow-up.
- Result: adverse reactions reported by 33% on lamotrigine, 44% on levetiracetam, 45% on zonisamide.
- Funding: independent (UK National Institute for Health Research)
ARs were reported by 33% of participants starting lamotrigine, 44% starting levetiracetam and 45% starting zonisamide.
The US label's boxed warning records serious rash requiring hospitalisation, including Stevens-Johnson syndrome, at roughly 0.3% to 0.8% in children aged 2 to 17 and 0.08% to 0.3% in adults. (Source 2)
- Official position, Certainty not rated.
- Size: not stated; pooled clinical trial and postmarketing experience.
- Who: patients aged 2 years and over treated with lamotrigine.
- How long: nearly all life-threatening rashes occur within 2 to 8 weeks of starting, though isolated cases have followed prolonged treatment.
- Result: serious rash approximately 0.3% to 0.8% in pediatric patients aged 2 to 17 years and 0.08% to 0.3% in adults.
- Funding: regulatory position (US FDA-approved labelling, DailyMed version dated 2023-05-08)
The incidence of these rashes, which have included Stevens-Johnson syndrome, is approximately 0.3% to 0.8% in pediatric patients (aged 2 to 17 years) and 0.08% to 0.3% in adults receiving lamotrigine.
The label also records that haemophagocytic lymphohistiocytosis, a life-threatening immune activation syndrome with a high death rate, has occurred in children and adults taking lamotrigine. (Source 12)
- Official position, Certainty not rated.
- Size: not stated; postmarketing case reports.
- Who: pediatric and adult patients taking lamotrigine for various indications.
- How long: not stated in the label passage recorded.
- Result: no rate given in the label passage recorded.
- Funding: regulatory position (US FDA-approved labelling, DailyMed version dated 2023-05-08)
HLH is a life-threatening syndrome of pathologic immune activation characterized by clinical signs and symptoms of extreme systemic inflammation.
What the evidence supports
Cochrane found that adding lamotrigine to existing treatment in drug-resistant focal epilepsy probably increases the chance of at least halving seizure frequency by about 80% in relative terms. (Source 3)
- Systematic review, Moderate certainty.
- Size: 1322 participants across 12 trials for the primary outcome; 1806 participants across 14 studies in total (38 infants, 199 children, 1569 adults)
- Who: infants, children and adults with drug-resistant focal (partial-onset) epilepsy; five parallel-group studies, eight cross-over studies and one responder-enriched parallel study in infants.
- How long: baseline phases four to 12 weeks, treatment phases eight to 36 weeks.
- Result: RR 1.80, 95% CI 1.45 to 2.23 for 50% or greater reduction in seizure frequency; moderate-certainty evidence.
- Funding: Cochrane review, independent; included trials largely industry sponsored.
Lamotrigine compared with placebo probably increases the likelihood of achieving 50% or greater reduction in seizure frequency (RR 1.80, 95% CI 1.45 to 2.23; 12 trials, 1322 participants (adults and children); moderate-certainty evidence).
In SANAD II's per-protocol analysis, counting only people who took their allocated drug as prescribed, lamotrigine was superior to both levetiracetam and zonisamide. (Source 13)
- Randomized trial, High certainty.
- Size: 990 participants in the focal epilepsy trial (per-protocol subset not stated in the passage recorded)
- Who: people aged 5 years and over with newly diagnosed focal epilepsy.
- How long: followed up for a further 2 years after recruitment closed in June 2017.
- Result: lamotrigine superior to levetiracetam HR 1.32, 97.5% CI 1.05 to 1.66; superior to zonisamide HR 1.37, 95% CI 1.08 to 1.73.
- Funding: independent (UK National Institute for Health Research)
Limit of this finding: The report prints 97.5% confidence intervals throughout except for zonisamide in the per-protocol sentence, where it prints a 95% interval. Comparing a 95% interval with a 97.5% one in the same sentence is not like for like, so the zonisamide per-protocol interval should be read as slightly narrower than the others rather than as a directly comparable figure. The two analyses of this trial point in different directions, and the report gives both. Counting everyone as randomised, zonisamide came out non-inferior to lamotrigine; counting only those who took the drug as prescribed, lamotrigine came out better than both comparators. The trial's own conclusion rests on the second. A reader should treat 'lamotrigine was not bettered' as the safe reading and should not conclude that zonisamide was shown to be equivalent.
The per-protocol (PP) analysis found superiority of lamotrigine over both levetiracetam (HR 1.32, 97.5% CI 1.05 to 1.66) and zonisamide (HR 1.37, 95% CI 1.08 to 1.73).
SANAD II concluded that its findings do not support using levetiracetam or zonisamide instead of lamotrigine as first-line treatment for focal epilepsy. (Source 14)
- Randomized trial, High certainty.
- Size: 990 participants in the focal epilepsy trial.
- Who: people aged 5 years and over with newly diagnosed focal epilepsy.
- How long: at least 2 years of follow-up.
- Result: no separate estimate; the trial's own conclusion on first-line choice.
- Funding: independent (UK National Institute for Health Research)
Limit of this finding: The two analyses of this trial point in different directions, and the report gives both. Counting everyone as randomised, zonisamide came out non-inferior to lamotrigine; counting only those who took the drug as prescribed, lamotrigine came out better than both comparators. The trial's own conclusion rests on the second. A reader should treat 'lamotrigine was not bettered' as the safe reading and should not conclude that zonisamide was shown to be equivalent.
The SANAD II findings do not support the use of levetiracetam or zonisamide as first-line treatments in focal epilepsy.
An independent individual-patient meta-analysis of five manufacturer-funded trials found a modest benefit of lamotrigine over placebo in bipolar depression, needing 11 people treated for one extra responder. (Source 6)
- Meta-analysis, Moderate certainty.
- Size: 1,072 patients across five randomised controlled trials.
- Who: adults with bipolar depression, type I or II.
- How long: acute treatment trials.
- Result: HRSD response RR 1.27 (95% CI 1.09 to 1.47), NNT 11 (95% CI 7 to 25); MADRS response RR 1.22 (95% CI 1.06 to 1.41), NNT 13 (95% CI 7 to 33)
- Funding: industry-funded trials (GlaxoSmithKline), independent analysis.
Limit of this finding: The wording quoted here is the summary the UK Centre for Reviews and Dissemination wrote for its DARE database, not the study authors' own prose. The figures are CRD's report of the study. Anyone checking the original paper will find it worded differently.
The NNT to achieve one more response than placebo was 11 (95% CI 7 to 25) using the HRSD and 13 (95% CI 7 to 33) using the MADRS.
What the evidence does not support
In the same review there was probably no difference between lamotrigine and placebo in fatigue, or in the number of people who stopped treatment for any reason. (Source 3)
- Systematic review, Moderate certainty.
- Size: 1552 participants across 12 studies for fatigue; 1806 across 14 trials for treatment withdrawal.
- Who: people with drug-resistant focal epilepsy.
- How long: treatment phases eight to 36 weeks.
- Result: fatigue RR 0.82 (99% CI 0.55 to 1.22); treatment withdrawal for any reason RR 1.11 (95% CI 0.91 to 1.37)
- Funding: Cochrane review, independent.
There is probably little or no difference in the risk of fatigue between lamotrigine and placebo (RR 0.82, 99% CI 0.55 to 1.22; 12 studies, 1552 participants; moderate-certainty evidence).
In the same bipolar depression analysis there was no significant difference in how many people stopped treatment on lamotrigine compared with placebo. (Source 15)
- Meta-analysis, Moderate certainty.
- Size: 1,072 patients across five randomised controlled trials.
- Who: adults with bipolar depression, type I or II.
- How long: acute treatment trials.
- Result: no significant difference in discontinuation rates; no significant interaction between bipolar I or II subgroup and treatment effect.
- Funding: industry-funded trials (GlaxoSmithKline), independent analysis.
Limit of this finding: The wording quoted here is the summary the UK Centre for Reviews and Dissemination wrote for its DARE database, not the study authors' own prose. The figures are CRD's report of the study. Anyone checking the original paper will find it worded differently.
There was no significant difference in discontinuation rates between lamotrigine and placebo, nor in interaction between diagnostic subgroup (bipolar I and II) and treatment effect.
For treatment-resistant unipolar depression, a systematic review found lamotrigine augmentation made no difference on depression rating scales and rested almost entirely on uncontrolled studies. (Source 7)
- Systematic review, Very low certainty.
- Size: 289 patients across ten studies, of which only one was a randomised controlled trial with 23 patients, 15 of them with unipolar depression; individual study sizes ranged from 14 to 42 patients.
- Who: adults with unipolar depression that had not responded to antidepressants.
- How long: the single RCT ran 42 days; the rest were retrospective chart reviews and open-label studies.
- Result: no differences between groups on mean HAM-D, MADRS or GAF scores; a significant difference only on the CGI severity scale in the single RCT (2.15 ± 1.28 versus 3.40 ± 1.17, p=0.0308)
- Funding: not stated in the passage recorded.
Limit of this finding: The wording quoted here is the summary the UK Centre for Reviews and Dissemination wrote for its DARE database, not the study authors' own prose. The figures are CRD's report of the study. Anyone checking the original paper will find it worded differently.
There were no differences between the groups for mean HAM-D scores, MADRS scores or GAF scores.
The same review concluded there was little evidence to guide use of lamotrigine for depression that had not responded to antidepressants. (Source 16)
- Systematic review, Very low certainty.
- Size: 289 patients across ten studies.
- Who: adults with treatment-resistant unipolar depression.
- How long: mostly short-term.
- Result: no pooled estimate; the review judged the evidence preliminary and drawn from retrospective and open-label studies.
- Funding: not stated in the passage recorded.
Limit of this finding: The wording quoted here is the summary the UK Centre for Reviews and Dissemination wrote for its DARE database, not the study authors' own prose. The figures are CRD's report of the study. Anyone checking the original paper will find it worded differently.
There was little evidence to guide the use of lamotrigine for depression that had not responded to a course of anti-depressants.
Where the evidence is mixed
The same review states that its trials were relatively short and give no long-term evidence, and that some of them had few participants. (Source 17)
- Systematic review, Moderate certainty.
- Size: 14 studies, 1806 participants.
- Who: people with drug-resistant focal epilepsy.
- How long: treatment phases eight to 36 weeks; no long-term data.
- Result: no effect estimate; the review's own statement about the limits of its evidence base.
- Funding: Cochrane review, independent.
The trials were of relatively short duration and provided no long-term evidence. In addition, some trials had few participants.
For drug-resistant generalised tonic-clonic seizures Cochrane found lamotrigine almost doubled the chance of halving seizure frequency, but rated this low certainty and could not settle whether it produced seizure freedom. (Source 5)
- Systematic review, Low certainty.
- Size: 300 participants across three studies; the pooled dichotomous outcomes come from the two parallel-group studies (270 participants)
- Who: children and adults with drug-resistant primary generalised tonic-clonic seizures.
- How long: two parallel-group studies and one cross-over study.
- Result: 50% or greater seizure reduction RR 1.88 (95% CI 1.43 to 2.45), low certainty; seizure freedom RR 1.55 (95% CI 0.89 to 2.72), very low certainty; treatment withdrawal RR 1.20 (95% CI 0.72 to 1.99), very low certainty.
- Funding: Cochrane review, independent.
Participants taking lamotrigine were almost twice as likely to attain a 50% or greater reduction in primary generalised tonic-clonic seizure frequency than those taking a placebo (RR 1.88, 95% CI 1.43 to 2.45; low-certainty evidence).
The authors of that review say they are uncertain to very uncertain that their own results are accurate and that the true effect could be grossly different. (Source 18)
- Systematic review, Very low certainty.
- Size: 300 participants across three studies.
- Who: people with drug-resistant generalised tonic-clonic seizures.
- How long: short trials.
- Result: no effect estimate; the review's own judgement that it provides insufficient information to inform clinical practice.
- Funding: Cochrane review, independent.
Therefore, we are uncertain to very uncertain that the results reported are accurate, and suggest that the true effect could be grossly different.
In the SANAD II non-inferiority trial of newly diagnosed focal epilepsy, levetiracetam failed to meet the non-inferiority criterion against lamotrigine in the primary intention-to-treat analysis of time to 12-month remission, while zonisamide did meet it. (Source 4)
- Randomized trial, High certainty.
- Size: 990 participants in the focal epilepsy trial; about 1,510 across both SANAD II trials (990 focal, 520 generalised or unclassifiable)
- Who: people aged 5 years and over with newly diagnosed focal epilepsy.
- How long: recruited April 2013 to June 2017 and followed up for a further 2 years; the endpoint was time to 12-month remission.
- Result: non-inferiority margin HR 1.329; levetiracetam versus lamotrigine HR 1.18, 97.5% CI 0.95 to 1.47 (criterion not met); zonisamide versus lamotrigine HR 1.03, 97.5% CI 0.83 to 1.28 (criterion met)
- Funding: independent (UK National Institute for Health Research)
Limit of this finding: The trial's own sentence puts '(HR 1.329)' immediately after the words 'criteria for non-inferiority', where it reads like levetiracetam's result. It is not: 1.329 is the pre-agreed limit a drug had to stay under to count as non-inferior, and levetiracetam's own hazard ratio, 1.18, appears later in the same sentence. Read 1.329 as the bar, not as a finding. The two analyses of this trial point in different directions, and the report gives both. Counting everyone as randomised, zonisamide came out non-inferior to lamotrigine; counting only those who took the drug as prescribed, lamotrigine came out better than both comparators. The trial's own conclusion rests on the second. A reader should treat 'lamotrigine was not bettered' as the safe reading and should not conclude that zonisamide was shown to be equivalent.
Levetiracetam did not meet the criteria for non-inferiority (HR 1.329) in the primary intention-to-treat (ITT) analysis of time to 12-month remission [HR vs. lamotrigine 1.18, 97.5% confidence interval (CI) 0.95 to 1.47], but zonisamide did meet the criteria (HR vs. lamotrigine 1.03, 97.5% CI 0.83 to 1.28).
All five trials in that bipolar depression meta-analysis were funded by the manufacturer. (Source 19)
- Meta-analysis, Moderate certainty.
- Size: 1,072 patients across five trials.
- Who: adults with bipolar depression.
- How long: acute treatment trials.
- Result: no effect estimate; a funding and quality observation recorded in a separate Funding field of the review record.
- Funding: industry-funded (GlaxoSmithKline)
Limit of this finding: The wording quoted here is the summary the UK Centre for Reviews and Dissemination wrote for its DARE database, not the study authors' own prose. The figures are CRD's report of the study. Anyone checking the original paper will find it worded differently.
Trials were funded by GlaxoSmithKline, no additional funding was received.
Where the research disagrees
Whether lamotrigine works for depression
- Geddes and colleagues, independent individual-patient meta-analysis of five randomised trials in bipolar depression, meta-analysis of individual patient data from five industry-funded randomised trials, 1072 patients: Lamotrigine could be effective for treatment of acute bipolar depression, type I or II, and for the prevention of relapse. (Source 20)
- Systematic review of lamotrigine augmentation in treatment-resistant unipolar depression, systematic review of ten studies, 289 patients, only one randomised controlled trial: There was little evidence to guide the use of lamotrigine for depression that had not responded to a course of anti-depressants. (Source 16)
How much
- Reference intake: There is no reference intake for a medicine. Dose is set by the prescriber and is escalated slowly because of the rash risk, which the label states is concentrated in the first 2 to 8 weeks. (Source 2)
- Upper limit: As a position, the US labelling states that for bipolar disorder doses above 200 mg/day are not recommended, because trials of up to 400 mg/day as monotherapy showed no additional benefit over 200 mg/day. This ceiling is specific to bipolar maintenance dosing and is not a general ceiling for lamotrigine. (Source 21)
- Studied: The add-on epilepsy trials pooled by Cochrane enrolled 1806 participants in total; the doses used in individual trials were not given in the review summary we could reach, so no studied dose is reported here. (Source 3)
- Studied: The bipolar depression trials pooled in the individual-patient meta-analysis included 1,072 patients across five randomised trials; the review record we could reach did not state the doses used. (Source 6)
A common belief, and what the research shows
The belief: Lamotrigine is an antidepressant, so it should help ordinary (unipolar) depression too.
What the research shows: The randomised evidence for depression is in bipolar disorder, and even there it is modest: the independent meta-analysis found "The NNT to achieve one more response than placebo was 11 (95% CI 7 to 25) using the HRSD and 13 (95% CI 7 to 33) using the MADRS." For unipolar treatment-resistant depression the review found "There were no differences between the groups for mean HAM-D scores, MADRS scores or GAF scores." Its strongest evidence is in epilepsy.
Questions and answers
What is it?
Lamotrigine is a prescription anticonvulsant tablet, chemically a phenyltriazine. It is approved both for several kinds of epilepsy and for maintenance treatment of bipolar I disorder to delay new mood episodes. It carries a boxed warning about serious rash. (Source 22)
What does it do in the body?
It blocks voltage-sensitive sodium channels on nerve cells, which stabilises membranes that are firing too readily and reduces the release of excitatory transmitters such as glutamate. That is how it is understood to suppress seizures. The label says the mechanism behind its effect in bipolar disorder is not established. (Source 1)
Is it good or bad for you?
In epilepsy the balance is favourable: Cochrane found it probably increases the chance of halving seizures (RR 1.80) and in SANAD II it caused fewer adverse reactions than its comparators. The serious risk is rash in the first weeks, quantified in the boxed warning, and it also causes more ataxia, dizziness, double vision and nausea than placebo. For depression outside bipolar disorder the evidence does not support benefit. (Source 3)
How do you get more of it?
This does not apply as it would to a nutrient: lamotrigine is prescription-only and the dose is set and escalated by a prescriber. The escalation is deliberately slow because nearly all life-threatening rashes occur in the first 2 to 8 weeks, and the label states that for bipolar disorder doses above 200 mg/day are not recommended. (Source 2)
If it is harmful, what reduces it?
If lamotrigine is causing harm, the exposure is reduced by a prescriber stopping or reducing it, and unless safety demands speed the label's position is a taper of at least two weeks. Certain interacting medicines also change how much circulates: valproate more than doubles the level. (Source 10)
Why might someone be low in it or missing it?
Nobody is deficient in lamotrigine; it is not made by the body. A person's blood level can fall, though, for documented reasons: estrogen-containing oral contraceptives speed its clearance and lower its concentration, and stopping the drug removes it entirely, which in epilepsy can bring seizures back. (Source 9)
Which whole foods contain it or feed it?
No whole food contains lamotrigine and we found no documented food or supplement interaction for it in the sources we reached. The documented interactions in the label are with other medicines, chiefly valproate and estrogen-containing contraceptives, which change its blood level. (Source 9)
We searched: Searched the US label sections on drug interactions and clinical pharmacology, the Cochrane add-on epilepsy review and the SANAD II report; none documents a food, alcohol or supplement interaction with lamotrigine, only interactions with other medicines.
What happens if you do not have it?
For someone with epilepsy who needs it, going without means losing the seizure reduction the trials measured, and the label warns that removing it may increase seizure frequency. For someone with bipolar I disorder the approved purpose is to delay new mood episodes; the measured benefit in bipolar depression was modest, with 11 people treated for one extra responder. (Source 10)
How can you test for it?
The sources we reached do not describe a validated blood test used to decide whether someone needs lamotrigine; trials measured seizure frequency and depression rating scales instead. Blood levels are known to change with valproate and with estrogen-containing contraceptives, which is why concentrations are sometimes checked clinically. (Source 3)
We searched: Searched the Cochrane add-on focal epilepsy review, the SANAD II NIHR report, the bipolar depression individual-patient meta-analysis and the US label; the outcomes reported are seizure frequency and rating scales, and no validated diagnostic test threshold is given.
References
- DailyMed (US National Library of Medicine), FDA-approved labelling, document version dated 2023-05-08. LAMOTRIGINE tablet — section 12.1 Mechanism of Action, the sodium-channel paragraph. 2023. Read the source
- DailyMed (US National Library of Medicine), FDA-approved labelling, document version dated 2023-05-08. LAMOTRIGINE tablet — the complete BOXED WARNING (WARNING: SERIOUS SKIN RASHES), transcribed from DailyMed on 2026-09-23. 2023. Read the source
- Cochrane Database of Systematic Reviews 2023, Issue 12, Art. No.: CD001909. Lamotrigine add-on therapy for drug-resistant focal epilepsy — Main results section of the abstract, in full. 2023. DOI 10.1002/14651858.CD001909.pub4. Read the source
- NIHR Journals Library (Health Technology Assessment), NCBI Bookshelf NBK575842. Lamotrigine versus levetiracetam or zonisamide for focal epilepsy and valproate versus levetiracetam for generalised and unclassified epilepsy: two SANAD II non-inferiority RCTs — focal epilepsy Results, the non-inferiority sentence. 2021. Read the source
- Cochrane Database of Systematic Reviews 2020, Issue 6, Art. No.: CD007783. Lamotrigine as add-on therapy for drug-resistant generalised tonic-clonic seizures — Main results section of the abstract, in full. 2020. DOI 10.1002/14651858.CD007783.pub3. Read the source
- Database of Abstracts of Reviews of Effects (DARE), Centre for Reviews and Dissemination (UK), NCBI Bookshelf NBK76826. The wording quoted here is CRD's own structured abstract, NOT the text of the original paper (British Journal of Psychiatry 2009;194(1):4-9, PubMed 19118318), whose published abstract is worded differently.. DARE structured abstract of: Geddes JR, Calabrese JR, Goodwin GM. Lamotrigine for treatment of bipolar depression: independent meta-analysis and meta-regression of individual patient data from five randomised trials — 'Results of the review' field, first two paragraphs. 2009. Read the source
- Database of Abstracts of Reviews of Effects (DARE), Centre for Reviews and Dissemination (UK), NCBI Bookshelf NBK79680. The wording quoted here is CRD's own structured abstract, NOT the text of the original review (Journal of Mental Health 2010;19(2):168-175, PubMed 20433324).. DARE structured abstract of: Thomas SP, Nandhra HS, Jayaraman A. Systematic review of lamotrigine augmentation of treatment resistant unipolar depression (TRD) — 'Results of the review' field, first two paragraphs. 2010. Read the source
- Drugs.com reproduction of the FDA-approved prescribing information, revision noted as 5/2026. Lamotrigine prescribing information — Drug Interactions, valproate. 2026. Read the source
- DailyMed (US National Library of Medicine), FDA-approved labelling, document version dated 2023-05-08. LAMOTRIGINE tablet — section 5.8 Concomitant Use with Oral Contraceptives. 2023. Read the source
- DailyMed (US National Library of Medicine), FDA-approved labelling, document version dated 2023-05-08. LAMOTRIGINE tablet — section 5.9 Withdrawal Seizures, in full. 2023. Read the source
- NIHR Journals Library (Health Technology Assessment), NCBI Bookshelf NBK575842. Two SANAD II non-inferiority RCTs — focal epilepsy Results, the adverse reactions sentence. 2021. Read the source
- DailyMed (US National Library of Medicine), FDA-approved labelling, document version dated 2023-05-08. LAMOTRIGINE tablet — section 5.2 Hemophagocytic Lymphohistiocytosis, opening sentences. 2023. Read the source
- NIHR Journals Library (Health Technology Assessment), NCBI Bookshelf NBK575842. Two SANAD II non-inferiority RCTs — focal epilepsy Results, the per-protocol analysis sentence. 2021. Read the source
- NIHR Journals Library (Health Technology Assessment), NCBI Bookshelf NBK575842. Two SANAD II non-inferiority RCTs — the focal epilepsy conclusion sentence. 2021. Read the source
- Database of Abstracts of Reviews of Effects (DARE), Centre for Reviews and Dissemination (UK), NCBI Bookshelf NBK76826. CRD's wording, not the original paper's.. DARE structured abstract of Geddes et al., lamotrigine for bipolar depression — 'Results of the review' field, third paragraph (discontinuation and severity subgroup). 2009. Read the source
- Database of Abstracts of Reviews of Effects (DARE), Centre for Reviews and Dissemination (UK), NCBI Bookshelf NBK79680. CRD's wording, not the original review's.. DARE structured abstract of Thomas et al., lamotrigine augmentation in treatment-resistant unipolar depression — 'Authors' conclusions' field. 2010. Read the source
- Cochrane Database of Systematic Reviews 2023, Issue 12, Art. No.: CD001909. Lamotrigine add-on therapy for drug-resistant focal epilepsy — Authors' conclusions section of the abstract, in full. 2023. DOI 10.1002/14651858.CD001909.pub4. Read the source
- Cochrane Database of Systematic Reviews 2020, Issue 6, Art. No.: CD007783. Lamotrigine as add-on therapy for drug-resistant generalised tonic-clonic seizures — Authors' conclusions section of the abstract, in full. 2020. DOI 10.1002/14651858.CD007783.pub3. Read the source
- Database of Abstracts of Reviews of Effects (DARE), Centre for Reviews and Dissemination (UK), NCBI Bookshelf NBK76826. CRD's wording, not the original paper's.. DARE structured abstract of Geddes et al., lamotrigine for bipolar depression — 'Funding' field. 2009. Read the source
- Database of Abstracts of Reviews of Effects (DARE), Centre for Reviews and Dissemination (UK), NCBI Bookshelf NBK76826. CRD's wording, not the original paper's.. DARE structured abstract of Geddes et al., lamotrigine for bipolar depression — 'Authors' conclusions' field. 2009. Read the source
- Drugs.com reproduction of the FDA-approved prescribing information, revision noted as 5/2026. Lamotrigine prescribing information — section 2.4 Bipolar Disorder, the 400 mg/day and 200 mg/day dosing passage (this ceiling is specific to bipolar maintenance dosing, not a global ceiling for lamotrigine). 2026. Read the source
- Drugs.com reproduction of the FDA-approved prescribing information, revision noted as 5/2026. Lamotrigine prescribing information — section 1.2, the bipolar I disorder maintenance indication. 2026. Read the source